Muscle Physiology: Skeletal, Smooth, & Cardiac Muscle Types, Histology, & 4 Cardinal Properties
Histological Triad of Muscle Tissue: Skeletal, Cardiac, & Smooth
Cellular morphology, nuclear positioning, striation patterns, and autonomic vs. somatic innervation
Introduction: What is Muscle Tissue?
Muscle may be defined as the primary contractile tissue of the human body. Muscle tissue is composed of highly differentiated, specialized cells packed with contractile proteins (predominantly actin and myosin). The biochemical structural biology of these myofilaments generates the mechanical pulling forces necessary for cellular contraction, which drives movement within internal organs and propels the body as a whole through locomotion.
Embryologically, the vast majority of muscle cells originate from the mesoderm (the middle embryonic germ layer). Their cellular differentiation occurs principally through a gradual process of lengthening and cytoplasmic elongation. In healthy adults, muscle tissue is massive in scale, constituting approximately 40% to 50% of total body weight.
The Muscle Cell (Myocyte)
A myocyte (also known as a muscle cell or muscle fiber) represents the basic structural and functional cellular unit of muscle tissue. Muscle cells are uniquely equipped with intracellular protein filaments that slide past one another in an ATP-dependent manner, producing a mechanical contraction that alters both the length and the shape of the cell.
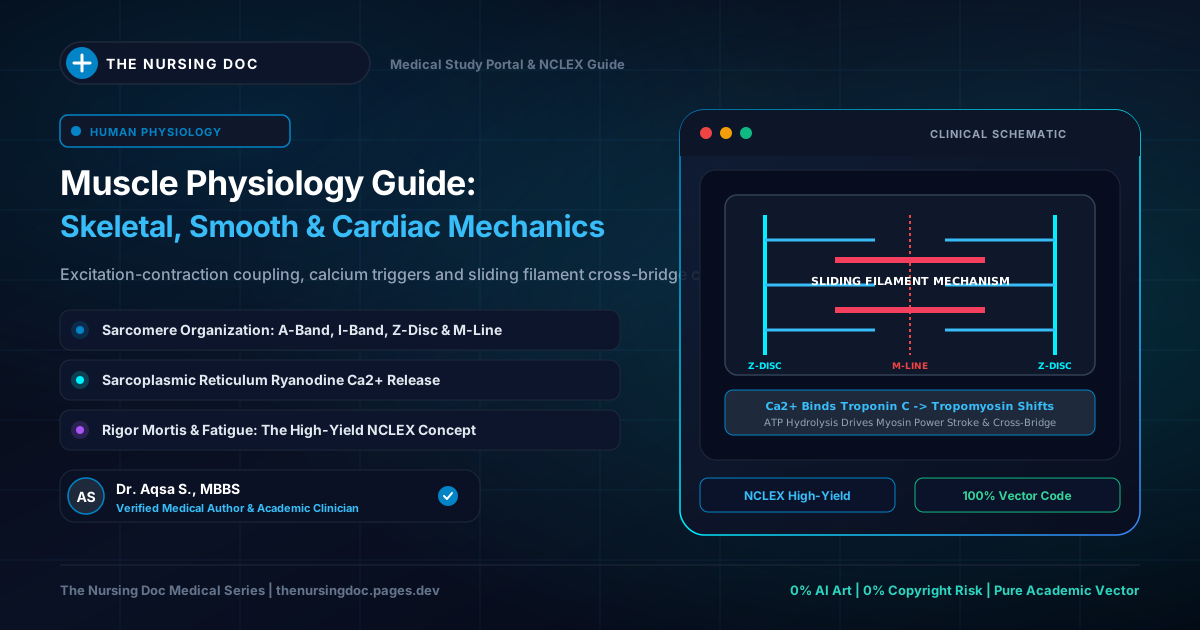
Figure 1: Molecular Architecture of Contractile Myofilaments
Thin Actin Filaments (5–7 nm) vs. Thick Myosin Filaments (10–15 nm)
Histologically and physiologically, human myocytes diverge into three specialized categories:
1. Smooth Muscle (Visceral & Involuntary)
Smooth muscle is so named because its individual fibers do not show cross striations under microscopic examination. Smooth muscle is primarily distributed within the tunica media of blood vessel walls (arteries and arterioles) and the walls of hollow abdominopelvic viscera (gastrointestinal tract, urinary bladder, ureters, and uterus), where its primary physiological duty is to modulate luminal caliber and propel luminal contents.
2. Skeletal Muscle (Somatic & Voluntary)
Skeletal muscle forms the macroscopic flesh and edible meat of the body. In fresh anatomical dissection, it displays a characteristic pinkish-red hue due to high vascularity and rich myoglobin oxygen-binding pigment. Individual skeletal muscle fibers do not function alone; they are organized into discrete structural bundles called fasciculi, enveloped by dense connective tissue sheaths (epimysium, perimysium, and endomysium).
3. Cardiac Muscle (Myocardium & Involuntary Syncytium)
Cardiac muscle is uniquely involuntary yet striated, residing exclusively within the thick wall of the heart (myocardium). Cardiac myocytes are arranged in long serial chains connected end-to-end by highly specialized junctional complexes termed intercalated discs. The fibers branch and anastomose extensively, creating a continuous functional syncytium that allows a single action potential to sweep rapidly across the entire heart chamber.
The 4 Cardinal Physiological Properties of Muscle
To perform mechanical work without sustaining structural damage, all muscle tissue exhibits four cardinal functional attributes:
Figure 2: Functional Quadrant of Muscle Tissue
Excitability, Contractility, Extensibility, and Elasticity
⚡ 1. Excitability (Irritability)
The capacity of muscle tissue to perceive and respond to chemical or mechanical stimuli. A stimulus initiates a localized shift in membrane electrical potential across the sarcolemma, triggering a propagating wave of depolarization (action potential).
✊ 2. Contractility
The quintessential hallmark of muscle: the active ability to generate mechanical tension, thicken, and shorten when stimulated by an adequate threshold impulse, doing physiological mechanical work.
↔️ 3. Extensibility
The ability of muscle tissue to be lengthened or stretched without structural disruption or tearing. Smooth muscle displays supreme extensibility (e.g., the stomach expanding after a meal or the urinary bladder expanding with urine).
🪀 4. Elasticity
The passive elastic rebound property that permits a contracted or distended muscle fiber to recoil and return to its original resting anatomical length and configuration once tension ceases.
Major Physiological Functions of Muscle
1. Production of Motion (Voluntary & Involuntary)
Muscles drive physical locomotion (walking, running, grasping), vocalization, respiration (diaphragm and intercostal action), cardiac blood ejection through the vascular tree, and involuntary visceral peristalsis moving boluses through the digestive tract.
2. Maintenance of Posture & Body Position
Even when stationary, continuous, low-level isometric contractions (known as muscle tone) stabilize the vertebral column and joints, preventing collapse against gravity during standing or sitting.
3. Thermogenesis (Heat Production & Thermoregulation)
Because ATP hydrolysis during cross-bridge cycling is thermodynamically inefficient, mechanical contraction releases massive thermal energy. It is clinically established that up to 80% of all basal and active human body heat is generated by skeletal muscle contractions. Rapid involuntary rhythmic twitches (shivering thermogenesis) serve as the body's primary acute defense against hypothermia.
Bedside Nursing Application & NCLEX Clinical Pearls
Muscle physiology directly governs critical bedside nursing evaluations across emergency, surgical, and cardiac units:
Severe trauma, crush injuries, or prolonged immobility rupture the sarcolemma, releasing toxic levels of myoglobin and potassium into the bloodstream. Nurses must monitor for tea-colored urine and aggressively hydrate to prevent myoglobin precipitation in renal tubules.
During an acute myocardial infarction (MI), ischemic necrosis of cardiac myocytes breaks down sarcomeric integrity, leaking Cardiac Troponin I (cTnI) and Troponin T (cTnT) into circulation. Troponins remain elevated for up to 10–14 days, serving as the gold standard bedside biomarker.
General anesthesia and surgical bowel manipulation temporarily paralyze intestinal smooth muscle (paralytic ileus). Nurses must auscultate bowel sounds in all 4 quadrants and confirm flatus/stool passage before advancing patients from NPO to solid oral nutrition.
Quick-Review Summary: The 3 Muscle Types Comparison
| Feature | Skeletal Muscle | Cardiac Muscle | Smooth Muscle |
|---|---|---|---|
| Cell Shape | Long, cylindrical syncytium | Branching, Y-shaped cells | Fusiform (tapered at both ends) |
| Nucleus Position | Multiple, peripheral rim | Single (or dual), central oval | Single, central rod-shaped |
| Cross Striations | Present (Crisp) | Present | Absent (Smooth) |
| Special Junctions | None (independent fibers) | Intercalated discs (Gap junctions) | Gap junctions, dense bodies |
| Neural Control | Somatic motor (Voluntary) | Autonomic + SA node (Involuntary) | Autonomic & Hormonal (Involuntary) |
| Contraction Speed | Fast; fatigues rapidly | Moderate rhythmic; fatigue-resistant | Slow, sustained; fatigue-proof |
| Primary Location | Attached to bones of skeleton | Heart wall (Myocardium) | Blood vessels, GI tract, bladder, uterus |
Curated and medically verified by Dr. Aqsa S. for nursing students.
← Back to All Study Notes